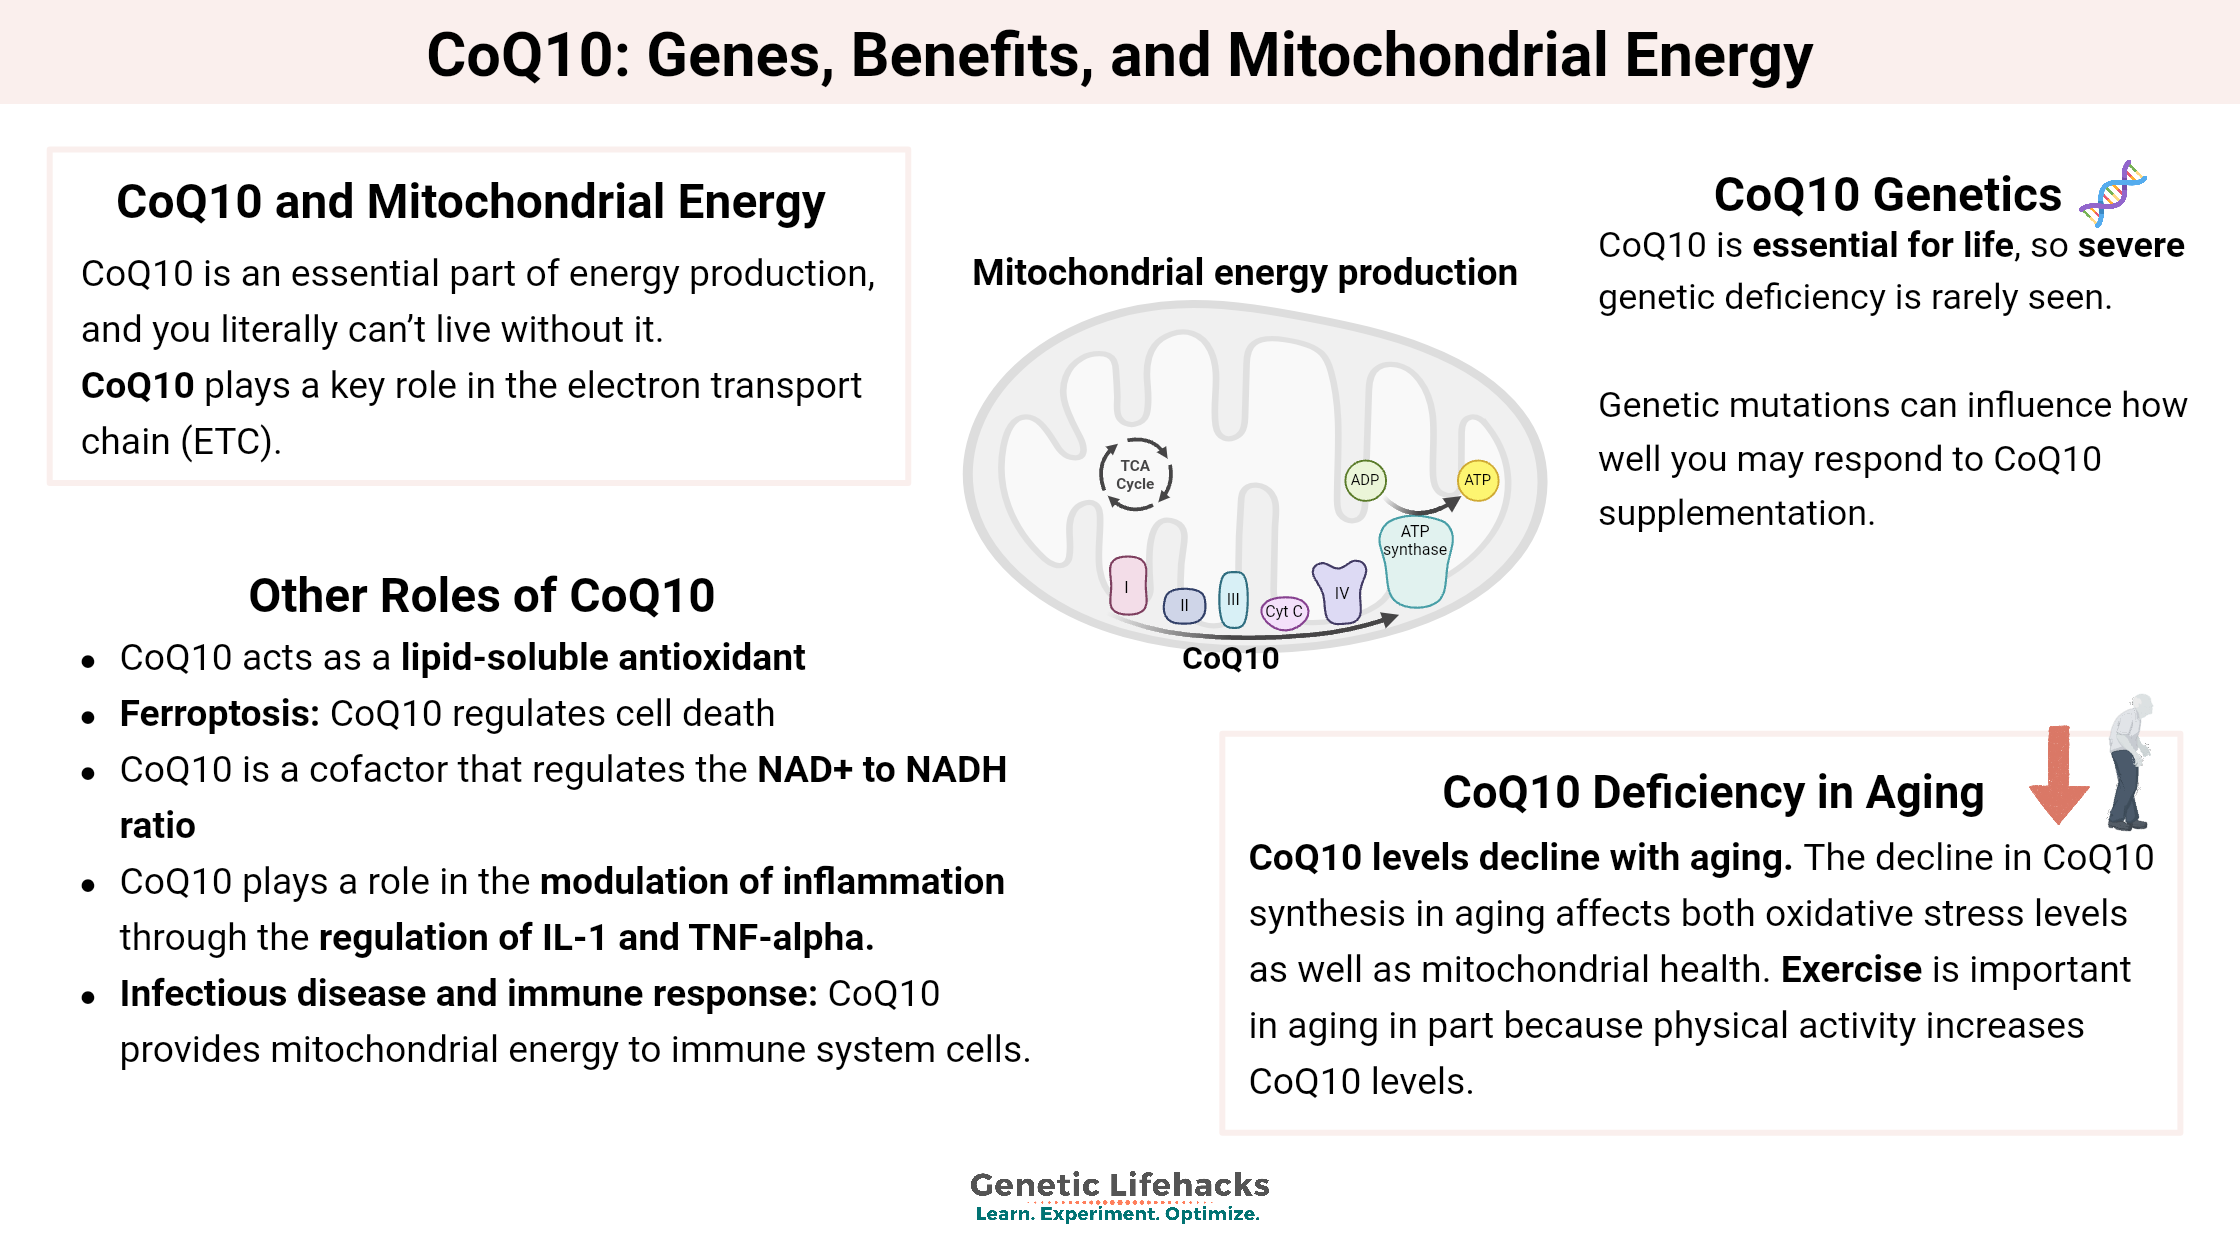
CoQ10 is essential for mitochondrial energy (ATP) production.
In addition, CoQ10 acts as an antioxidant, protecting against neuroinflammation and cell death.
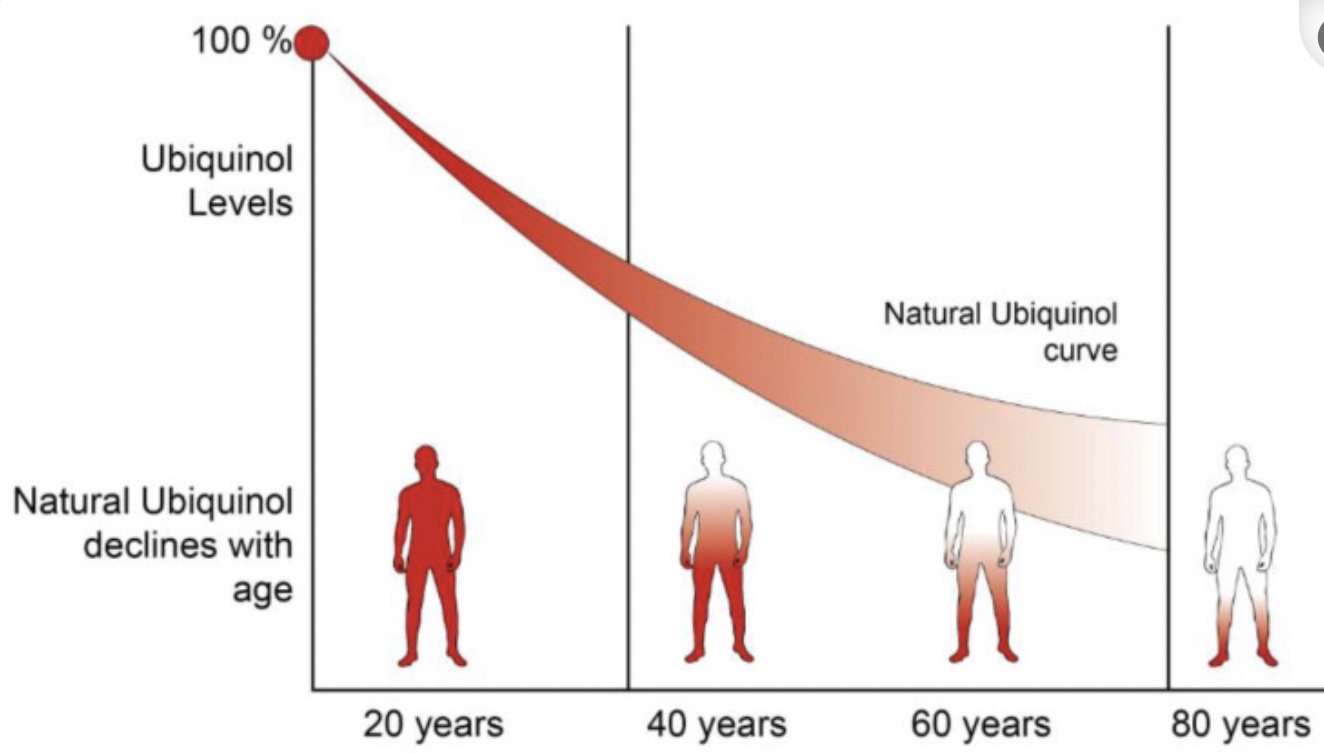
CoQ10 levels generally decrease with age, and optimizing CoQ10 levels may help with aging. Common medications can interfere with CoQ10 production.
Genetic variants can also impact Coenzyme Q10 levels and the efficacy of CoQ10 supplements.
Members will see their genotype report below and the solutions in the Lifehacks section. Consider joining today.
Understanding Coenzyme Q10 (CoQ10): Key Roles and Health Benefits
Coenzyme Q, called CoQ10 or ubiquinone, is a fundamental part of how your cells make ATP for energy. From plants to yeast to all animal cells, coenzyme Q is essential for all forms of life.
Let’s dig into what CoQ10 does and how to optimize it for cellular health.
CoQ10 and Mitochondrial Energy
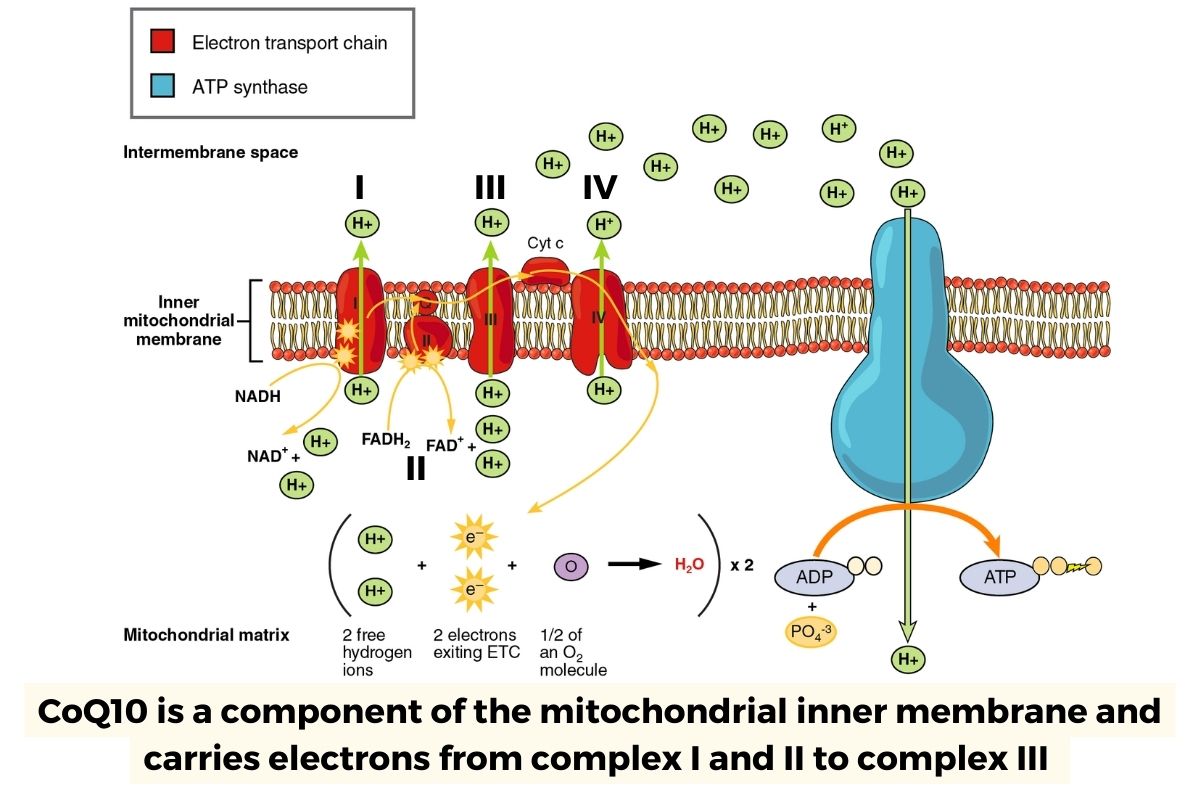
Within cells, mitochondria produce most of the ATP used for cellular energy through the electron transport chain (ETC).
The ETC is a series of protein complexes, called complexes I through IV, that transfer electrons via redox reactions. This process creates a proton gradient across the mitochondrial membrane, which is used for ATP synthesis.
CoQ10 plays a key role in the ETC as an electron carrier, shuttling electrons from complexes I and II to complex III.[ref] Coenzyme Q is also known as ubiquinone. This name refers to its ubiquitous presence in all animal cells. In humans, CoQ10 is the most common form of coenzyme Q, referring to its 10 isoprenyl subunits. Other animals have different numbers of subunits, such as mice, which primarily produce CoQ9.
Beyond mitochondrial energy – CoQ10’s other roles in health
CoQ10 is an essential part of energy production, and you literally can’t live without it. But that is only part of the story.
Like many molecules in the body, CoQ10 is used by cells for multiple purposes. Being able to move electrons and act in redox reactions lets it function in several ways — limiting free radicals and linking several processes of aging.
Here are some of the roles CoQ10 plays:
Antioxidant properties of CoQ10
In its reduced form, CoQ10 acts as a lipid-soluble antioxidant, which allows it to neutralize oxidative stress within cells.[ref] Importantly, as a lipid-soluble antioxidant, CoQ10 can help to prevent the oxidation of LDL cholesterol.[ref][ref]
Ferroptosis: CoQ10 in regulating cell death
A type of regulated cell death, ferroptosis involves the accumulation of iron and ROS in a cell to cause apoptosis (cell death). CoQ10 is one of the ways that cells stop ferroptosis and regulate cell death.[ref]
Regulation of NAD+/NADH
CoQ10 is also a cofactor that regulates the NAD+ to NADH ratio within the plasma membrane redox system. The NAD+ ratio is another essential part of how cells function and maintain cellular health.[ref]
CoQ10 plays a role in the modulation of inflammation through the regulation of IL-1 and TNF-alpha. Studies show that supplemental CoQ10 also reduces CRP and IL-6.[ref]
A 2024 study showed that CoQ10 supplementation after a heart attack helped to suppress excessive inflammation in the heart muscle. It did this by partially reducing the activation of the NLRP3 inflammasome.[ref]
Research shows that supplemental CoQ10 helps the immune response against pathogens, such as in sepsis and viral myocarditis. It takes a lot of energy to mount an immune response, so one role CoQ10 plays is to provide mitochondrial energy to immune system cells. In addition, as a lipid-soluble antioxidant, CoQ10 helps protect cells from cellular destruction caused by high levels of ROS in the immune response. Studies also show that in elderly patients with influenza, CoQ10 (200mg/day) reduces the severity and duration of illness. [ref]
In a large population study (4.5 million people), researchers investigated which current medications or supplements were associated with reduced severity and reduced risk of Covid-19. One of the strongest associations was CoQ10 supplementation, which was associated with an 85%reduced risk of hospitalization in Covid patients.[ref] There are, of course, possibilities of confounding variables with the Covid study, but the size of that risk reduction makes it probable that there is a strong signal there.
Neuroinflammation and epilepsy
Oxidative stress in the brain can cause neuroinflammation, and CoQ10 is a potent antioxidant. Patients with epilepsy have lower serum CoQ10 levels, on average, and CoQ10 plus seizure medications are more effective in reducing the frequency and duration of seizures. In Parkinson’s, though, clinical trials have shown mixed results.[ref][ref][ref]
Why the heart loves CoQ10
The heart is a very energy-intensive organ, constantly beating and needing a constant supply of ATP to relax and contract. CoQ10 is essential for ATP production in the mitochondria of the cardiomyocytes (heart muscle cells), and it also helps limit oxidative damage in the tissue. CoQ10 is also important in preventing LDL-c oxidation, playing a role in keeping the blood vessels in the heart clear and healthy.[ref]
CoQ10 may also help to protect the heart from environmental stressors. Animal studies show that supplemental CoQ10 before exposure to toxins, such as pesticides or industrial solvents, specifically helps to prevent damage to the heart.[ref]
The richest source of CoQ10 from foods is heart muscle meat, such as beef heart.
Understanding CoQ10 Deficiency: Risks and Symptoms
With CoQ10 playing so many roles in health, it is unsurprising that low CoQ10 levels can negatively impact wellness in many ways.
Rare gene mutations and CoQ10 deficiency: CoQ10 is essential for life, so a severe genetic deficiency is rarely seen. In other words, CoQ10 is something you literally can’t live without, so a severe deficiency is incompatible with life. People with low or insufficient levels of CoQ10 may experience effects on the heart, brain, and more.
Rare genetic mutations that cause partial CoQ10 deficiency can have a big impact on health, causing encephalopathy, stroke, cerebral ataxia, spasticity, deafness, retinopathy, or intellectual disability.
Less severe CoQ10 genetic deficiency can cause exerciseintolerance, muscular weakness, and ataxia later in life. Some genetic CoQ10 deficiency syndromes can be treated with high doses of supplemental CoQ10.[ref]
CoQ10 deficiency is fairly common in aging
In aging, CoQ10 deficiency or insufficiency may be more common. Levels generally decline in aging due to a reduction in CoQ10 synthesis. Studies show that older adults of both sexes often have lower serum CoQ10 concentrations and a decrease in CoQ10 redox capacity.[ref] One theory of aging is that mitochondrial dysfunction and excessive production of reactive oxygen species (ROS) are integral causes of aging and age-related diseases. As we age, mitochondria in cells have decreased functionality and decreased proliferation. Overall, this would lead to a decrease in cellular health and bioenergetics.[ref]
Immune function in aging:
Animal studies show that CoQ10 restoration in older mice helps reverse the loss of B-cell and T-cell function, which is a part of aging and immunosenescence.[ref]
Paired with selenium for antioxidant function:
A clinical trial in elderly adults showed that CoQ10 plus selenium supplementation was associated with fewer days in the hospital and better physical performance and vitality over a four-year study. [ref] A 2025 randomized double-blind, placebo-controlled trial found that 200 mg/day of CoQ10 plus 200 ug/day of selenium improved the 10-year cardiovascular survival rate, especially in women. [ref]
Brain energy in aging:
Genetic studies suggest that CoQ10 may play a significant role in neurodegenerative diseases. A genome-wide association study identified several genes that are linked to slightly lower serum CoQ10 levels. These genes are also implicated in Alzheimer’s disease and dementia.[ref] A study in patients with dementia showed that 73% had low CoQ10 levels, and those with low CoQ10 had higher serum amyloid beta levels.[ref]
Healthy heart in aging:
Most people associate supplemental CoQ10 with heart disease, and the heart needs a lot of CoQ10 for energy production, which is especially important in aging hearts. The anti-inflammatory effects of CoQ10 are thought to protect against cardiovascular disease.[ref]
Can supplementing with CoQ10 improve mitochondrial function in aging?
A small clinical trial using 200 mg/2x/day of a CoQ10 supplement (type unknown) showed that it increased serum levels but not mitochondrial levels in muscle tissue.[ref] Another clinical trial using 100mg/day of supplemental CoQ10 (type unknown) in older adults showed that it improved lower-body strength but not other exercise performance results.[ref]
Statins block the pathway involved in CoQ10 production
Statins are the most prescribed class of drugs in the U.S., and statins act to block the mevalonate pathway involved in both LDL and CoQ10 production.[ref]
A meta-analysis that involved data from 12 RCTs found that statins clearly reduce circulating CoQ10 levels. This reduction of CoQ10 was seen with all statin types and with low-, medium-, or high-intensity statins.[ref]
A 2026 study looked at more than 250,000 adults aged 40 and older in two big datasets, which contain genetic information and electronic health records. After the researchers statistically incorporated factors like age, BMI, APOE type, diabetes, and heart disease, the people who used statins had a little over twice the risk of dementia. High-intensity statins carried about 14% more risk than moderate- or low-intensity statins. The data also contained CoQ7 levels, and dementia risk correlated with lower CoQ7 levels. Note that the researchers only included study participants who had identified as White, and ancestry may be very important here.[ref] Not all studies show that link between statins and dementia risk. Other studies, including a 2025 meta-analysis with mixed ancestry groups, found no increased risk or even a protective effect.[ref] Another 2026 study involving 1200 people of mixed ancestry (25% Black) also showed no increase in risk of dementia from statins.[ref]
Migraines: People with migraines have lower levels of CoQ10, and a small placebo-controlled clinical trial showed that CoQ10 reduced migraine frequency, severity, and duration.[ref]
CFS/ME: Studies of chronic fatigue syndrome (ME/CFS) patients show a decrease in ATP synthesis and an increase in oxidative stress. Randomized, controlled trials of CoQ10 in ME/CFS show promise with decreased fatigue. However, it appears that CoQ10 helps a little, but doesn’t cure ME/CFS.[ref]
Parkinson’s: In Parkinson’s disease, the study results for CoQ10 are mixed. Trials with high doses, such as 1000 – 1200 mg/day, seem to show benefit, but these are really high doses. This would be a ‘talk to your doctor’ situation for someone with Parkinson’s.[ref]
Insulin resistance may also tie into low CoQ10. The inflammation and hyperinsulinemia are thought to prevent the expression of CoQ10 synthesis enzymes and reduce biosynthesis. This then leads to mitochondrial changes with excess ROS.[ref] A study in adults with pre-diabetes showed that 8 weeks of CoQ10 significantly reduced HOMA-IR levels, a marker for insulin resistance. However, there was no effect on HbA1c or fasting glucose.[ref] A 2026 meta-analysis of randomized placebo-controlled trials found that CoQ10 had a moderate beneficial effect on glycemic control biomarkers. [ref]
PCOS: In women with PCOS, CoQ10 supplementation lowers triglycerides, and a combination of CoQ10 and vitamin E reduces other lipid and hormonal levels.[ref]
More on clinical trials with CoQ10 in the Lifehacks section below. This molecule truly touches so many aspects of health.
The Biosynthesis of CoQ10 in Cells
The synthesis of coenzyme Q10 within cells is a complex process that involves multiple steps and genes.
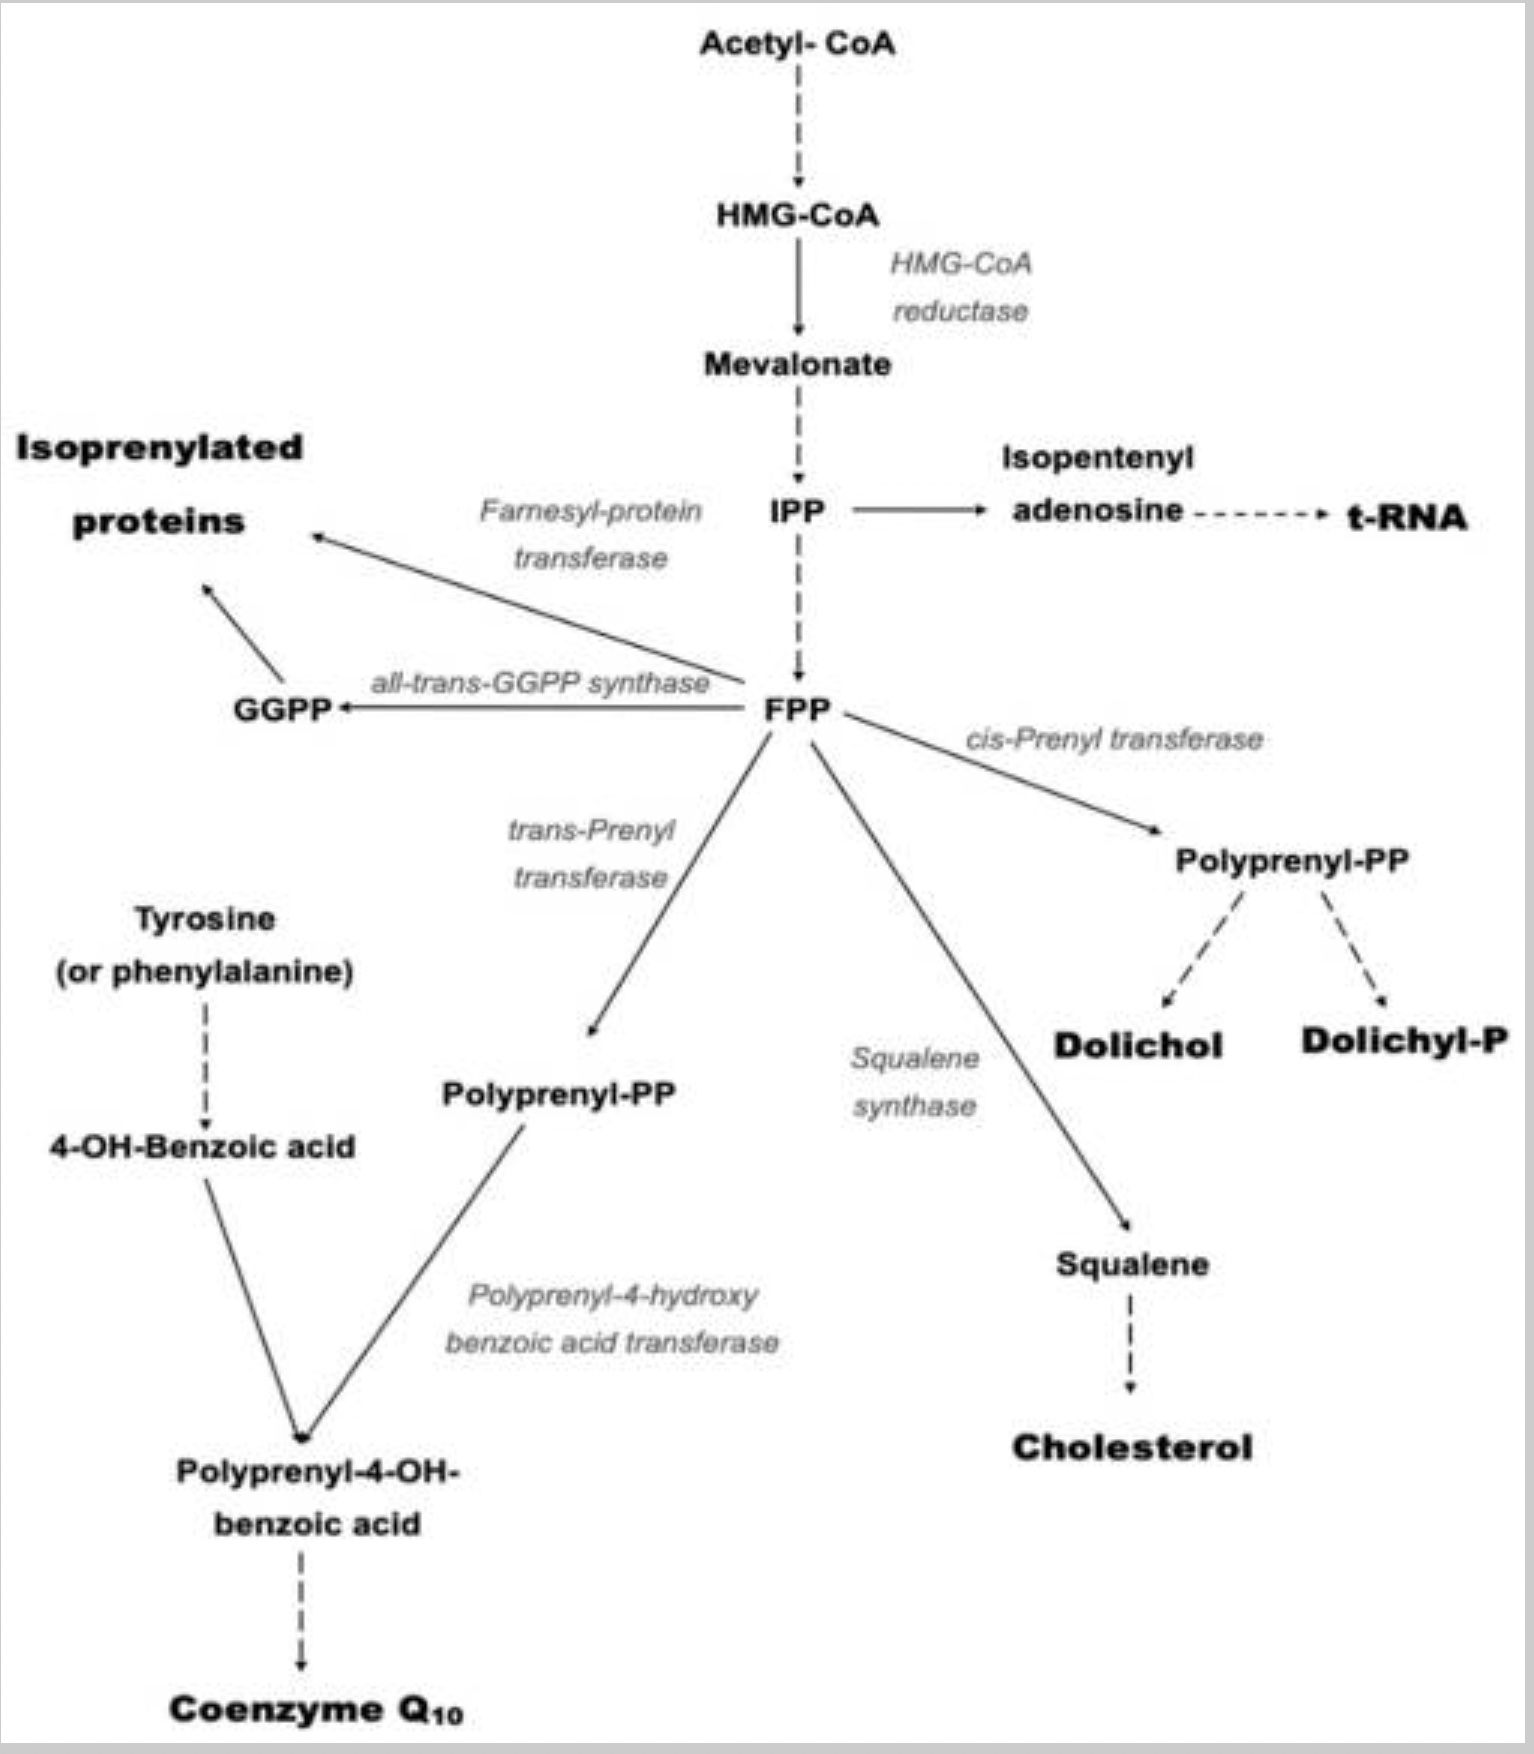
1) The first step is the synthesis of benzoquinone from a derivative of either tyrosine or phenylalanine. Phenylalanine is an essential amino acid that we get from foods containing protein, and tyrosine is an amino acid that the body makes from phenylalanine.
2) A polyisoprenoid side chain is synthesized from acetyl-CoA via the mevalonate pathway. The mevalonate pathway is also involved in cholesterol synthesis and is the pathway inhibited by statins.
3) A final step is condensing the benzoquinone with the polyisoprenoid side chains to form coenzyme Q. In humans, CoQ10 is the most common form with 10 isoprenoid side chains.[ref] In the mitochondria, COQ7 catalyzes the final hydroxylation step in the CoQ10 biosynthetic pathway.[ref]
In addition to cellular synthesis, most people get about 5 mg/day of CoQ10 from their diet. Organ meats tend to have the highest levels of CoQ10, but many other foods can add CoQ10 in small amounts. However, CoQ10 absorption from food isn’t great, and the body’s biosynthesis pathways are the main source of the molecule.
Genetic Influences on CoQ10 Synthesis and Deficiency
The genes involved in the Coenzyme Q biosynthesis pathway include CoQ1 through CoQ11 (named for the date of identification), PDSS1, and PDSS2.[ref]
Primary coenzyme Q10 deficiency is rare and, if detected early enough (usually in infancy), can often be treated with CoQ10 supplementation. Mutations that severely limit CoQ10 production cause symptoms such as ataxia, encephalomyopathy, deafness, lactic acidosis, retinitis pigementosa, and hypertrophic cardiomyopathy. Again, a significant deficiency is going to be apparent early in life.[ref][ref]
Mutations that cause a less severe CoQ10 deficiency can cause problems with muscle control, walking, and balance in adulthood.
Single mutation carrier effects: One example is a case study of siblings who both had problems with writing (i.e. writer’s cramp) in their teens to 20s, which then progressed to problems riding a bike and eventually with walking. They were found to have a single mutation in one of the genes involved in CoQ10 biosynthesis.[ref]
Secondary CoQ10 deficiency results from genetic mutations that aren’t directly related to the synthesis of coenzyme Q. For example, mutations in genes related to tyrosine or phenylalanine, genes related to mitochondrial acyl-CoA synthesis, and certain genes related to heart disease.
In the genotype report section below, we’ll go through the specifics of these genetic variants.
Genotype Report: CoQ10
Rare mutations in CoQ10 synthesis genes:
Please keep in mind that not all of the possible mutations related to CoQ10 are covered here. The mutations and SNPs below are ones that are found in 23andMe or AncestryDNA data. Thus, you can’t use this to rule out a CoQ10 mutation. Keep in mind that 23andMe and AncestryDNA data are not guaranteed to be clinically accurate tests. If you or your doctor suspect a rare CoQ10-related mutation, a clinical-grade genetic test along with a specialist evaluation is needed.
Access this content:
An active subscription is required to access this content.
Lifehacks: Safety, Absorption and Sources of CoQ10
In this section, I’ll cover the different types of CoQ10 supplements (there’s a bunch), safety considerations, and clinical trials that involve CoQ10. The clinical trials give solid examples of conditions that may be helped with CoQ10.
Keep in mind that CoQ10 synthesis decreases with aging. The research studies on healthy younger adults show that they may not get as much benefit from CoQ10 supplements — unless they have a chronic disease that affects the mitochondria or a genetic mutation.
As always, talk with your doctor if you have medical questions about a supplement.
Safety and Absorption of Supplemental CoQ10
CoQ10 is generally well tolerated and considered safe at supplemental doses. Numerous clinical trials and safety studies show no serious adverse effects from supplemental CoQ10.[ref] Some individual reports mention upset stomach or intestinal issues are possible.
Who should be cautious and talk with a doctor first
There is a possibility of an interaction with Coumadin or warfarin – some articles say it could be a problem based on rat studies, while others say it doesn’t interact. If you are taking warfarin, please talk with your doctor and pharmacist about drug interactions with any supplements you take. Some websites also suggest that CoQ10 may interact with diabetes medications and some cancer treatments (as an antioxidant). Pregnancy and breastfeeding safety information is also lacking.
Absorption
CoQ10 is a lipid (fat) and is insoluble in water. It is also a large molecule. This causes limited intestinal absorption from food or supplements.
Divided doses (e.g. 100 mg, 2x/day) are more effective than a single dose (e.g. 200 mg). Absorption is also better when taken with food.[ref]
Animal studies on Huntington’s disease show that high doses can cross the blood-brain barrier and slightly increase CoQ10 levels in the brain.[ref]
No decrease in endogenous production
Importantly, taking supplemental CoQ10 does not decrease the body’s production of CoQ10.[ref]
Different types of CoQ10 supplements
When you go to the store or look online at CoQ10 supplements, you’ll see that there are several choices, all claiming to be the best.
Most CoQ10 gel cap formulations contain CoQ10 plus an oil to increase absorption. Be sure to check and see what type of oil is in the supplement. There are formulations with MCT oil versus cottonseed or soybean oil.
Ubiquinone vs Ubiquinol: Which is best?
Ubiquinone is just another name for CoQ10.
Ubiquinol refers to the reduced form of ubiquinone — reduced in the redox sense, meaning that it is primed to act as an antioxidant.
Ubiquinol in older adults
A study in older men found that ubiquinol was superior to ubiquinone for increasing CoQ10 levels. The results showed that both ubiquinone and ubiquinol were effective in increasing total CoQ10, but ubiquinol was slightly better.[ref]
While both ubiquinone and ubiquinol can increase CoQ10 levels, if your goal is to reduce oxidative stress, ubiquinol seems to have the edge.
Types and formulations
Crystal-free formulations of CoQ10 in lipid-based soft gels have better absorption than crystalline formulations. Both lipid-based options had better absorption than the dry powder formulations.[ref]
Oleogel is a form of CoQ10 dissolved in oil within a gel matrix. It was similar in absorption and bioavailability to other forms of CoQ10, with the advantage of being easier to consume for people with problems swallowing.[ref]
Water-soluble formulations of CoQ10 are also being developed. Q10Vital is one, and it has been shown to have improved bioavailability compared to soft gels with CoQ10 in soybean oil.[ref]
Additives to CoQ10 supplements
Some CoQ10 in oil formulations contain surfactants, such as polysorbate 80 or polyethylene glycol. This helps to increase absorption by essentially thinning the intestinal mucosa. While effective for increasing absorption, there could be other consequences of surfactants that thin the mucosa (translocation of bacteria, inflammation, etc).
Piperine, a black pepper derivative, is often used to enhance the bioavailability of natural supplements. One study found that piperine did not statistically increase CoQ10 levels more than a CoQ10 supplement without piperine.[ref]
MitoQ is a mitoquinone molecule that is said to target the mitochondria. A head-to-head trial of 20 mg of MitoQ compared to 200 mg of CoQ10 showed that both suppressed mitochondrial ROS, “with some indication that MitoQ may be more effective than CoQ10.”[ref] In patients with peripheral artery disease, an 80 mg dose of MitoQ improved vascular endothelial function and exercise capacity.[ref] MitoQ was tested in a clinical trial for Parkinson’s disease, and there was no beneficial effect.[ref]
Independent supplement testing and reviews
ConsumerLab.com is an independent supplement testing source. They tested 15 different CoQ10 and ubiquinol supplements to see if they matched their labeled amounts. The tests showed that all were close to the labeled amount, with the exception of one product that contained more than it should have.
The ConsumerLab picks for the best CoQ10 products (based on price and quality) were Qunol Ultra CoQ10, Puritan’s Pride, and Vitafusion. For ubiquinol, the Qunol Mega CoQ10 Ubiquinol was the top pick.[ref]
Dietary sources of CoQ10
Reindeer meat is extremely high in CoQ10 (if it’s available where you live). Beef heart and chicken liver are both excellent sources of CoQ10 on a per-gram basis.
If you don’t like organ meats, most beef and pork cuts contain some CoQ10, and mackerel is also a good source. Soybeans top the list for plant sources. Parsley is also quite high, but no one eats 100g of parsley at a time. [ref]
However, none of these foods (other than a few pounds of reindeer meat) come close to the 100+ mg you get in a CoQ10 supplement.
Exercise increases CoQ10
Exercise is important in aging in part because physical activity increases CoQ10 levels. It is a two-way street here, with low CoQ10 levels causing decreased muscle strength and energy levels – and thus decreased ability to exercise.[ref]
Testing CoQ10 Levels
Blood tests for CoQ10 levels are readily available. If you are going to supplement and want to track your changes, you may want to get an initial test done to see if supplementing with CoQ10 changes your levels. In the US, you can order your own lab tests online in most states. Just as an example, the CoQ10 test is $55 at UltaLabTests.
Clinical trials with supplemental CoQ10
If you’re dealing with chronic conditions like migraines or high lipid levels, CoQ10 may help.
Migraines (CoQ10 with riboflavin and magnesium)
In adults with migraines, the combination of CoQ10, riboflavin, and magnesium reduced the number of migraine days from 6 per month to 4 per month. It also reduced the severity of migraines.[ref]
A 12-week study used a combination of CoQ10, Bifidobacterium longum, red yeast rice, and niacin, compared to a placebo. The combination decreased LDL cholesterol by 25% and triglycerides by 16%.[ref] Another study in adults with high LDL and not on statins found that ubiquinol at 200mg/day reduced LDL oxidation and increased flow-mediated dilation.[ref]
A 2022 double-blind placebo-controlled trial tested the effects of 600 mg per day of ubiquinol and 15 mg per day of D-ribose. This was a four-way clinical trial using D-ribose + placebo, ubiquinol + placebo, D-ribose + ubiquinol, and then just placebo. The results showed that either D-ribose or ubiquinol (or the combo) was effective in reducing cardiomyopathy scores and also reducing B-type natriuretic peptides (BNP). [ref]
Healing from tooth extraction
A study involving people undergoing wisdom tooth extraction showed the efficacy of CoQ10 supplements in wound healing. The participants took either 100 mg/day CoQ10 or placebo after oral surgery. The CoQ10 group had significantly faster tissue healing and fewer dry sockets.[ref]
Male infertility:
Access this content:
An active subscription is required to access this content.
Amprosi, Matthias, et al. “Familial Writer’s Cramp: A Clinical Clue for Inherited Coenzyme Q10 Deficiency.” Neurogenetics, vol. 22, no. 1, 2021, pp. 81–86. PubMed Central, https://doi.org/10.1007/s10048-020-00624-3.
Cirilli, Ilenia, et al. “Role of Coenzyme Q10 in Health and Disease: An Update on the Last 10 Years (2010–2020).” Antioxidants, vol. 10, no. 8, Aug. 2021, p. 1325. PubMed Central, https://doi.org/10.3390/antiox10081325.
Costa, Inês, et al. “Molecular Mechanisms of Ferroptosis and Their Involvement in Brain Diseases.” Pharmacology & Therapeutics, vol. 244, Apr. 2023, p. 108373. ScienceDirect, https://doi.org/10.1016/j.pharmthera.2023.108373.
Crane, F. L., et al. “The Essential Functions of Coenzyme Q.” The Clinical Investigator, vol. 71, no. 8 Suppl, 1993, pp. S55-59. PubMed, https://doi.org/10.1007/BF00226841.
Danhauser, Katharina, et al. “Fatal Neonatal Encephalopathy and Lactic Acidosis Caused by a Homozygous Loss-of-Function Variant in COQ9.” European Journal of Human Genetics, vol. 24, no. 3, Mar. 2016, pp. 450–54. DOI.org (Crossref), https://doi.org/10.1038/ejhg.2015.133.
Degenhardt, Frauke, et al. “Genome-Wide Association Study of Serum Coenzyme Q10 Levels Identifies Susceptibility Loci Linked to Neuronal Diseases.” Human Molecular Genetics, vol. 25, no. 13, July 2016, pp. 2881–91. PubMed, https://doi.org/10.1093/hmg/ddw134.
Doimo, Mara, et al. “Genetics of Coenzyme Q10 Deficiency.” Molecular Syndromology, vol. 5, nos. 3–4, July 2014, pp. 156–62. PubMed Central, https://doi.org/10.1159/000362826.
Fischer, Alexandra, et al. “Association between Genetic Variants in the Coenzyme Q10 Metabolism and Coenzyme Q10 Status in Humans.” BMC Research Notes, vol. 4, July 2011, p. 245. PubMed Central, https://doi.org/10.1186/1756-0500-4-245.
Ghanbarzadeh, S., et al. “CoQ10 and L-Carnitine Attenuate the Effect of High LDL and Oxidized LDL on Spermatogenesis in Male Rats.” Drug Research, vol. 64, no. 10, Oct. 2014, pp. 510–15. PubMed, https://doi.org/10.1055/s-0033-1361176.
Gherardi, Gaia, et al. “CoQ10 and Resveratrol Effects to Ameliorate Aged-Related Mitochondrial Dysfunctions.” Nutrients, vol. 14, no. 20, Oct. 2022, p. 4326. PubMed Central, https://doi.org/10.3390/nu14204326.
Ghirlanda, G., et al. “Evidence of Plasma CoQ10-Lowering Effect by HMG-CoA Reductase Inhibitors: A Double-Blind, Placebo-Controlled Study.” Journal of Clinical Pharmacology, vol. 33, no. 3, Mar. 1993, pp. 226–29. PubMed, https://doi.org/10.1002/j.1552-4604.1993.tb03948.x.
Hargreaves, Iain, et al. “Disorders of Human Coenzyme Q10 Metabolism: An Overview.” International Journal of Molecular Sciences, vol. 21, no. 18, Sept. 2020, p. 6695. PubMed Central, https://doi.org/10.3390/ijms21186695.
Hernández-Camacho, Juan D., et al. “Coenzyme Q10 Supplementation in Aging and Disease.” Frontiers in Physiology, vol. 9, Feb. 2018, p. 44. PubMed Central, https://doi.org/10.3389/fphys.2018.00044.
Izadi, Azimeh, et al. “Independent and Additive Effects of Coenzyme Q10 and Vitamin E on Cardiometabolic Outcomes and Visceral Adiposity in Women With Polycystic Ovary Syndrome.” Archives of Medical Research, vol. 50, no. 2, Feb. 2019, pp. 1–10. PubMed, https://doi.org/10.1016/j.arcmed.2019.04.004.
Johansson, P., et al. “Improved Health-Related Quality of Life, and More Days out of Hospital with Supplementation with Selenium and Coenzyme Q10 Combined. Results from a Double Blind, Placebo-Controlled Prospective Study.” The Journal of Nutrition, Health & Aging, vol. 19, no. 9, Nov. 2015, pp. 870–77. PubMed, https://doi.org/10.1007/s12603-015-0509-9.
Mantle, David, Robert A. Heaton, et al. “Coenzyme Q10 and Immune Function: An Overview.” Antioxidants, vol. 10, no. 5, May 2021, p. 759. PubMed Central, https://doi.org/10.3390/antiox10050759.
Mantle, David, Lauren Millichap, et al. “Primary Coenzyme Q10 Deficiency: An Update.” Antioxidants, vol. 12, no. 8, Aug. 2023, p. 1652. PubMed Central, https://doi.org/10.3390/antiox12081652.
Multidisciplinary Digital Publishing Institute. (2025, June 5). Selenium and coenzyme Q10 supplementation and sex differences in cardiovascular mortality results from a prospective randomized double-blind placebo-controlled trial in elderly people low in selenium [Generative AI chat]. Antioxidants. https://pmc.ncbi.nlm.nih.gov/articles/PMC12190002/
Niklowitz, Petra, et al. “Coenzyme Q10 Serum Concentration and Redox Status in European Adults: Influence of Age, Sex, and Lipoprotein Concentration.” Journal of Clinical Biochemistry and Nutrition, vol. 58, no. 3, May 2016, pp. 240–45. PubMed Central, https://doi.org/10.3164/jcbn.15-73.
NM_014317.5(PDSS1):C.336+5G>T AND Not Provided – ClinVar – NCBI. https://www.ncbi.nlm.nih.gov/clinvar/RCV000197300.2/. Accessed 12 Jan. 2026.
Pallotti, Francesco, et al. “The Roles of Coenzyme Q in Disease: Direct and Indirect Involvement in Cellular Functions.” International Journal of Molecular Sciences, vol. 23, no. 1, Dec. 2021, p. 128. PubMed Central, https://doi.org/10.3390/ijms23010128.
Pastor-Maldonado, Carmen J., et al. “Coenzyme Q10: Novel Formulations and Medical Trends.” International Journal of Molecular Sciences, vol. 21, no. 22, Nov. 2020, p. 8432. PubMed Central, https://doi.org/10.3390/ijms21228432.
Qu, Hua, et al. “The Effect of Statin Treatment on Circulating Coenzyme Q10 Concentrations: An Updated Meta-Analysis of Randomized Controlled Trials.” European Journal of Medical Research, vol. 23, Nov. 2018, p. 57. PubMed Central, https://doi.org/10.1186/s40001-018-0353-6.
Richards, Sue, et al. “Standards and Guidelines for the Interpretation of Sequence Variants: A Joint Consensus Recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology.” Genetics in Medicine, vol. 17, no. 5, May 2015, pp. 405–24. DOI.org (Crossref), https://doi.org/10.1038/gim.2015.30.
Ross, David, et al. “Benzene Toxicity: The Role of the Susceptibility Factor NQO1 in Bone Marrow Endothelial Cell Signaling and Function.” Chemico-Biological Interactions, vol. 192, nos. 1–2, June 2011, pp. 145–49. PubMed Central, https://doi.org/10.1016/j.cbi.2010.10.008.
Sabbatinelli, Jacopo, et al. “Ubiquinol Ameliorates Endothelial Dysfunction in Subjects with Mild-to-Moderate Dyslipidemia: A Randomized Clinical Trial.” Nutrients, vol. 12, no. 4, Apr. 2020, p. 1098. PubMed, https://doi.org/10.3390/nu12041098.
Sifuentes-Franco, Sonia, et al. “Antioxidant and Anti-Inflammatory Effects of Coenzyme Q10 Supplementation on Infectious Diseases.” Healthcare, vol. 10, no. 3, Mar. 2022, p. 487. PubMed Central, https://doi.org/10.3390/healthcare10030487.
Takahashi, Michiyo, et al. “CYP7A1, NPC1L1, ABCB1, and CD36 Polymorphisms Associated with Coenzyme Q10 Availability Affect the Subjective Quality of Life Score (SF-36) after Long-Term CoQ10 Supplementation in Women.” Nutrients, vol. 14, no. 13, June 2022, p. 2579. PubMed Central, https://doi.org/10.3390/nu14132579.
Testai, Lara, et al. “Coenzyme Q10: Clinical Applications beyond Cardiovascular Diseases.” Nutrients, vol. 13, no. 5, May 2021, p. 1697. PubMed Central, https://doi.org/10.3390/nu13051697.
Yamamoto, Yuzo, et al. “Biological Interaction of Cigarette Smoking on the Association between Genetic Polymorphisms Involved in Inflammation and the Risk of Lung Cancer: A Case-Control Study in Japan.” Oncology Letters, vol. 13, no. 5, May 2017, pp. 3873–81. PubMed, https://doi.org/10.3892/ol.2017.5867.
Yoo, Ja-Young, and Keun-Sang Yum. “Effect of Coenzyme Q10 on Insulin Resistance in Korean Patients with Prediabetes: A Pilot Single-Center, Randomized, Double-Blind, Placebo-Controlled Study.” BioMed Research International, vol. 2018, July 2018, p. 1613247. PubMed Central, https://doi.org/10.1155/2018/1613247.
Zhu, Zhen-Guo, et al. “The Efficacy and Safety of Coenzyme Q10 in Parkinson’s Disease: A Meta-Analysis of Randomized Controlled Trials.” Neurological Sciences: Official Journal of the Italian Neurological Society and of the Italian Society of Clinical Neurophysiology, vol. 38, no. 2, Feb. 2017, pp. 215–24. PubMed, https://doi.org/10.1007/s10072-016-2757-9.
Zozina, Vladlena I., et al. “Coenzyme Q10 in Cardiovascular and Metabolic Diseases: Current State of the Problem.” Current Cardiology Reviews, vol. 14, no. 3, Aug. 2018, pp. 164–74. PubMed Central, https://doi.org/10.2174/1573403X14666180416115428.
About the Author:
Debbie Moon is a biologist, engineer, author, and the founder of Genetic Lifehacks where she has helped thousands of members understand how to apply genetics to their diet, lifestyle, and health decisions. With more than 11 years of experience translating complex genetic research into practical health strategies, Debbie holds a BS in engineering from Colorado School of Mines and an MSc in biological sciences from Clemson University. She combines an engineering mindset with a biological systems approach to explain how genetic differences impact your optimal health.